

Types of Hair Loss: A Field Guide for Stylists and Barbers
The main types of hair loss a stylist or barber may see in the chair, how scarring and non-scarring alopecia differ, and which patterns need a fast referral.
The main types of hair loss a stylist or barber will see are androgenetic alopecia, telogen effluvium, alopecia areata, traction alopecia, and two scarring conditions: central centrifugal cicatricial alopecia (CCCA) and frontal fibrosing alopecia. They split into non-scarring types, where the follicle survives, and scarring types, where it does not. That split decides how fast a client needs a doctor.
You see the same scalps every four to eight weeks, from angles the client never sees. That makes you the person most likely to spot a change early. This guide covers what each pattern may look like in the chair and how urgently to refer. It does not teach diagnosis. Recognize, support, refer.
What are the main types of hair loss a stylist will see?
Six types of hair loss cover most of what shows up in a salon or barbershop: androgenetic alopecia, telogen effluvium, alopecia areata, traction alopecia, CCCA and frontal fibrosing alopecia. The first four are non-scarring, at least early on. The last two are scarring alopecias that can cause permanent loss.
The American Academy of Dermatology (AAD) lists many more causes, including scalp infection, thyroid disease, medication side effects, scalp psoriasis and hair pulling. You do not need to sort all of them. You need to notice that something changed, describe it accurately, and know which patterns cannot wait.
What is the difference between scarring vs non-scarring alopecia?
In non-scarring alopecia the follicle is still there, so hair may regrow once the cause is addressed. In scarring alopecia, also called cicatricial alopecia, inflammation destroys the follicle and scar tissue takes its place. The AAD states that once a hair follicle is destroyed, it cannot regrow a hair.
That one fact sets your referral clock. A client with post-illness shedding has time. A client with an active scarring condition is losing follicles that will not come back, and the AAD says of CCCA that starting treatment early can prevent it from spreading outward and causing more permanent loss.
| Non-scarring alopecia | Scarring alopecia | |
|---|---|---|
| Follicle | Still present | Destroyed and replaced by scar tissue |
| Regrowth | May be possible | Not possible from destroyed follicles (AAD) |
| What the scalp may look like | Usually looks like normal skin | May look shiny and smooth in advanced areas |
| What the client may feel | Often nothing | Often itching, burning, tenderness or stinging |
| Examples | Androgenetic alopecia, telogen effluvium, alopecia areata, early traction alopecia | CCCA, frontal fibrosing alopecia |
| Referral urgency | Soon | Prompt, first available dermatology visit |
What does each type of alopecia look like in the chair?
Each type tends to follow a location and pattern. The table below pairs what you may observe with the typical pattern described by the AAD and MedlinePlus. Patterns overlap, two conditions can exist together, and only a dermatologist or physician can confirm a type. Use it to describe, not to label.
| Type | What it may look like in the chair | Typical pattern or location | Scarring? | Referral urgency |
|---|---|---|---|---|
| Androgenetic alopecia (pattern hair loss) | Wider part, more scalp showing on top, finer hairs mixed with thicker ones, receding temples in men | Men: receding hairline or bald spot on top. Women: overall thinning or a widening part (AAD) | No | Soon. The AAD notes results are better when care starts early |
| Telogen effluvium (excessive shedding) | Client reports handfuls in the shower, thinner ponytail, more hair in the bowl, no bald patches | All over the scalp, often a few months after childbirth, illness or a major stressor | No | Routine. Suggest a doctor if it continues or no trigger is clear |
| Alopecia areata | Round or oval, smooth bald patch on the scalp or beard, skin looks normal | Patches anywhere, sometimes a band of loss; the AAD notes no swelling or discoloration | No | Soon. New or spreading patches need a medical visit |
| Traction alopecia | Broken hairs at the forehead, receding edges, thinning where the style pulls | Hairline and wherever hair is pulled tight | Not at first; can become permanent (AAD) | Change the tension now. Refer if bumps, crusts, stinging or bare skin |
| CCCA | Breakage or thinning at the crown, tender or itchy scalp, later a shiny smooth patch | Starts in the center of the scalp and grows outward (AAD) | Yes | Prompt |
| Frontal fibrosing alopecia | Hairline moving back in a band, thinning or missing eyebrows | Front and sides of the hairline; eyebrows often involved (AAD) | Yes | Prompt |
Androgenetic alopecia
Androgenetic alopecia is the pattern type. MedlinePlus estimates it affects 50 million men and 30 million women in the United States. In men the hairline recedes from the temples into an M shape and the crown thins. In women the top thins and the part widens, and the hairline usually stays put. Under magnification you may see hairs of mixed thickness, which is covered in what hair miniaturization is.
Telogen effluvium
Telogen effluvium is excessive shedding, not patchy loss. The AAD says it is normal to shed 50 to 100 hairs a day, and that people shed far more after stressors such as childbirth, illness or major stress. Per the AAD, hair tends to regain its normal fullness within six to nine months after the stressor ends. See the telogen effluvium guide for stylists and the difference between hair shedding and hair loss.
Alopecia areata
The AAD describes alopecia areata as a round or oval, smooth balding patch on the scalp or beard, with no visible irritation where the hair is missing. About 10% to 20% of people with it also have nail changes such as tiny dents. Hair can grow back, and patches can also appear elsewhere. Barbers often find beard patches first. More detail is in the alopecia areata guide for stylists.
Traction alopecia
Traction alopecia comes from repeated pulling. The AAD lists early signs: broken hairs around the forehead, a receding hairline, patches where hair is pulled tight, pain, stinging, crusts, and tenting of the scalp. It is the one type on this list where your own work matters directly, because loosening the style is the first step. The AAD warns it can become permanent the longer it continues.
Which types of hair loss need a fast referral?
Scarring types need the fastest referral: CCCA and frontal fibrosing alopecia. Any pattern that comes with burning, pain, tenderness, bumps, crusting or a shiny smooth patch should also go to a dermatologist promptly. In these conditions follicles are being destroyed, and the AAD is clear that destroyed follicles cannot regrow hair.
CCCA
The AAD describes CCCA as the most common type of scarring hair loss for women of African descent, while noting it develops in men and in people of all races. It often begins as a small round patch in the center of the scalp that grows over time. Early signs can be subtle: breakage at the crown, tiny bumps, itching or tenderness. Read the full CCCA early signs guide.
Frontal fibrosing alopecia
Frontal fibrosing alopecia usually starts along the front and sides of the head and can look like a receding hairline. The AAD reports that between 80% and 95% of women diagnosed with it have lost some or all of their eyebrows, and that it mostly affects women after menopause. A hairline moving back together with thinning brows is a pattern worth mentioning to the client right away.
What should a stylist or barber do after noticing a pattern?
Describe what you see, ask one or two open questions, and suggest a medical visit matched to the urgency. Do not name a condition, recommend a treatment, or promise regrowth. Your value is the early catch and the calm conversation, which a client may not get anywhere else.
- Look. Check the part, crown, hairline, edges and nape under good light at every visit. A scalp scope helps you see and photograph detail.
- Record. Note location, size and any client-reported symptoms. Take photos with consent so you can compare next visit.
- Say what you see. "The part looks a little wider than it did in spring" is an observation. "You have female pattern hair loss" is a diagnosis.
- Ask. "Have you noticed any tenderness, itching or burning here?" Symptoms raise the urgency.
- Refer. Suggest a dermatologist or physician. For crown or hairline loss with symptoms, say it should not wait.
- Support. Adjust tension, heat and styling. Offer cosmetic options that add fullness without stress on the hair.
For wording, see how to talk to a client about hair loss and the list of signs in when to refer a client to a dermatologist.
How can you get better at recognizing types of hair loss?
Recognition improves with structured training and repetition. Learn the six types of hair loss above first, then practice describing location, pattern and scalp condition on every client, including the healthy ones. A normal scalp is your baseline. Without it, early change is easy to miss.
USTI's trichology pathway starts with the Hair Loss Practitioner course, a 2 day live virtual class with educators, and continues to Associate Trichologist and Clinical training. Barbers can start with the barber trichology course. Trichology training does not make you a medical provider. It makes you better at the three things this guide is built on: recognize the types of hair loss, support the client, refer early.
New to the field? Start with What is trichology? or look up a term in the trichology glossary.
Sources
- American Academy of Dermatology: Hair loss, who gets and causes
- American Academy of Dermatology: Central centrifugal cicatricial alopecia (CCCA)
- American Academy of Dermatology: Frontal fibrosing alopecia
- American Academy of Dermatology: Alopecia areata signs and symptoms
- American Academy of Dermatology: Hairstyles that pull can lead to hair loss
- MedlinePlus Genetics (NIH): Androgenetic alopecia
Frequently asked questions
What are the most common types of hair loss?
The types a stylist or barber is most likely to see are androgenetic alopecia (pattern hair loss), telogen effluvium (excessive shedding), alopecia areata (patchy loss), and traction alopecia (loss from repeated pulling). Scarring types such as CCCA and frontal fibrosing alopecia are less common but more urgent. Only a dermatologist or physician can confirm which type a client has.
What is the difference between scarring and non-scarring alopecia?
In non-scarring alopecia the hair follicle is still present, so regrowth may be possible. In scarring alopecia, also called cicatricial alopecia, inflammation destroys the follicle and scar tissue replaces it. The American Academy of Dermatology states that a destroyed follicle cannot regrow a hair, so early medical care matters most for scarring types.
Can a hairstylist tell a client what type of hair loss they have?
No. A stylist or barber can describe what they see, such as a wider part, a smooth round patch, or a receding hairline with eyebrow thinning, and suggest a medical visit. Naming the condition is a diagnosis, and diagnosis belongs to a dermatologist or physician. Many types look alike and some need a biopsy to confirm.
Which types of hair loss are permanent?
Scarring types, including CCCA and frontal fibrosing alopecia, can cause permanent hair loss because the follicle is destroyed. The American Academy of Dermatology also notes that traction alopecia can become permanent the longer the pulling continues. Shedding after a stressor is usually temporary, and hair can grow back in alopecia areata.
What does scarring alopecia look like in the salon?
According to American Academy of Dermatology pages on CCCA, a scarred area may look shiny and smooth. Earlier, a client may report itching, burning, tenderness or stinging, and there may be breakage, tiny bumps or scaling. These signs are not proof of scarring alopecia, but together they are a reason to suggest a prompt dermatology visit.
How fast should a client with possible scarring hair loss see a dermatologist?
As soon as they can get an appointment. The American Academy of Dermatology says starting treatment early can prevent CCCA from spreading and causing more permanent loss, and that frontal fibrosing alopecia treatment tends to work better the earlier it starts. Waiting several appointments to see if it clears up costs follicles that cannot be replaced.
This article is educational and is not medical advice. USTI teaches professionals to recognize, support and refer.
Turn this knowledge into a certification.
Learn hair and scalp science with USTI educators, from your first course to clinical training.
Explore trichology coursesRelated articles

Alopecia Areata: A Stylist's Guide to Bald Patches
Alopecia areata explained for stylists: the signs you may spot first, what to say when you find a bald patch on a client, cosmetic support and when to refer.

CCCA Hair Loss: Early Signs Every Stylist Should Know
CCCA hair loss often starts quietly at the crown. Learn the early signs a stylist may notice, how it differs from traction alopecia, and when to refer.
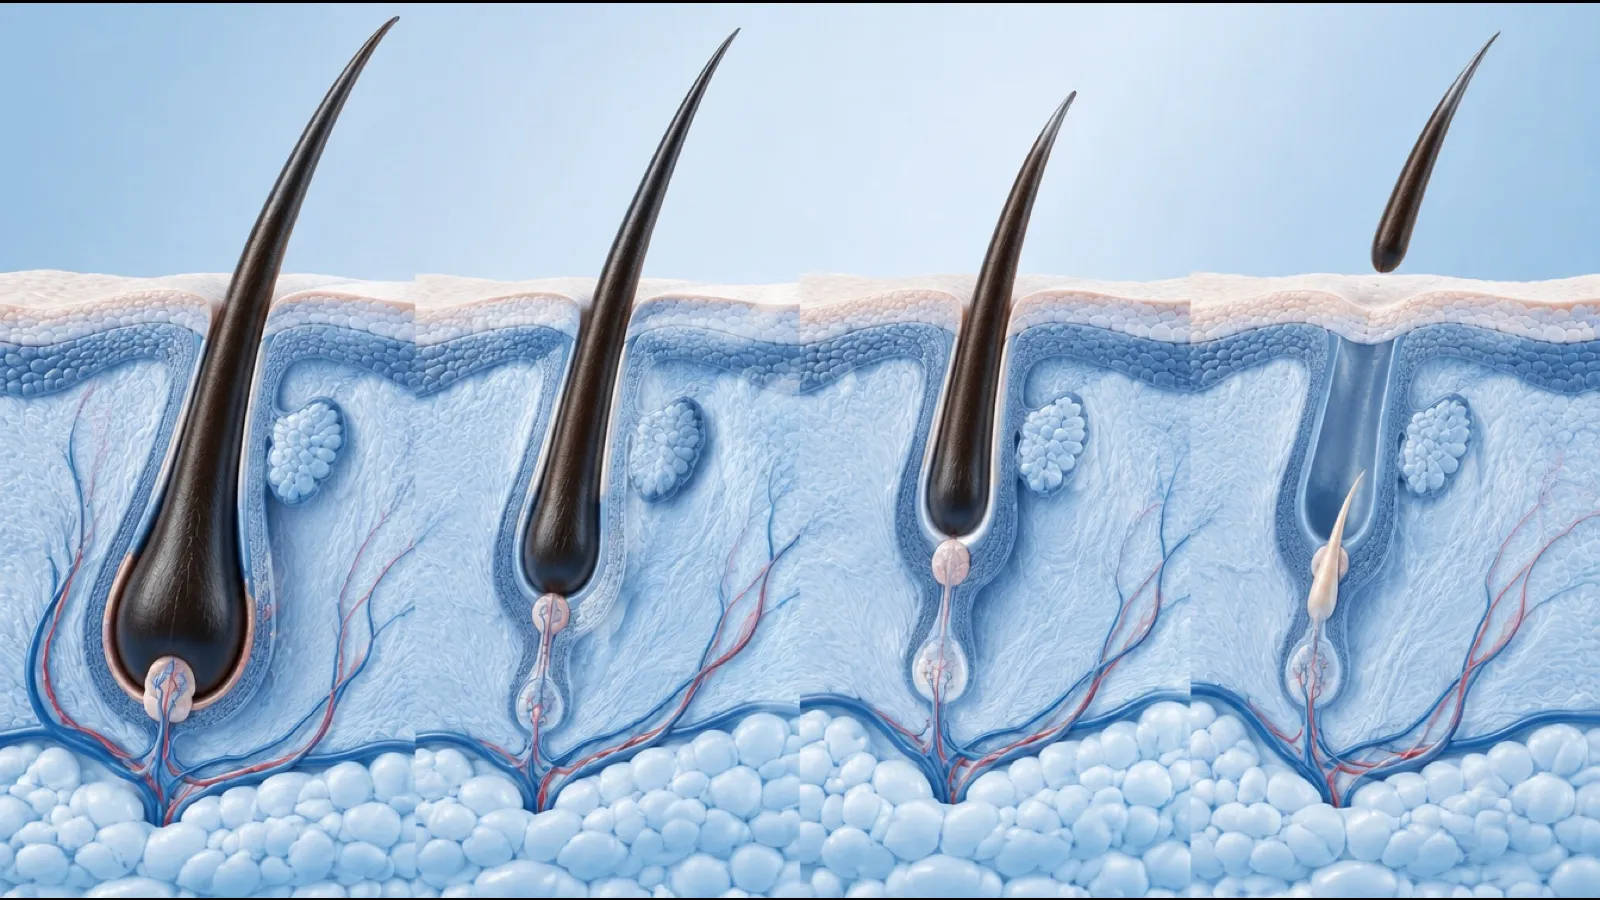
Hair Growth Cycle Stages: Anagen, Catagen, Telogen, Exogen
The hair growth cycle stages explained for stylists: anagen, catagen, telogen and exogen, how long each lasts by source and what the cycle means at the chair.